


A patient returns for follow-up after starting a GLP-1 receptor agonist. Their weight is down, but nausea has made meals unpredictable, and their insurer has declined the next refill. The GLP-1 trial results that helped start the conversation are still relevant. The decisions now depend on information the trial average cannot supply: whether the benefits matter to this patient, what the treatment is costing them in daily life, and whether they can continue it.
Start with the comparison behind GLP-1 trial results
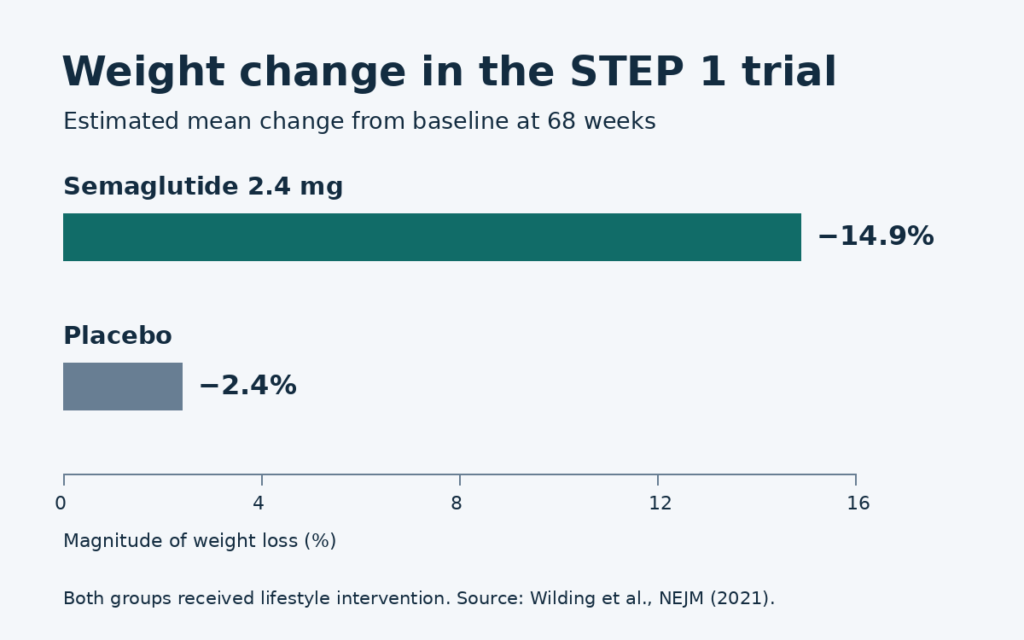
In STEP 1, 1,961 adults with obesity or overweight and a weight-related condition, without diabetes, were assigned to weekly subcutaneous semaglutide 2.4 mg or placebo. Both groups received a lifestyle intervention. At 68 weeks, estimated mean weight change was −14.9% with semaglutide and −2.4% with placebo [1]. The comparison matters because it shows the difference between the study groups under the conditions tested. The average also leaves room for substantial variation in individual experience.
Before quoting a percentage from GLP-1 trial results, check who enrolled, what the comparison group received, how long participants were followed, and how the researchers handled treatment discontinuation and missing data. Then ask whether the outcome matches the reason the patient sought treatment. Weight change may matter to someone who wants to walk farther or manage a weight-related condition. Progress toward that goal still needs its own measure. Asking how far the patient can walk now, or what they can do at work that was difficult before, can add information that a scale reading misses.
Use the follow-up visit to find out what changed
I would start by asking the patient what has improved and what has become harder. A person who describes better appetite control may also be skipping meals because eating brings on nausea. Another may tolerate treatment well and still have difficulty getting the next prescription filled. These situations call for different decisions even when the weight curves look similar.
Review the dose the patient is actually taking, recent changes, missed doses, and when symptoms occur. In STEP 1, gastrointestinal adverse events were the most common reason for discontinuation among participants who stopped because of adverse events [1]. At the visit, asking what someone managed to eat and drink yesterday can give a clearer picture than asking whether they are tolerating the medication. I would also ask about changes in strength, usual activity, and the patient’s ability to eat enough to support everyday function. The next decision should reflect those answers alongside the weight trend.
Ask about access before a refill runs out. Has the pharmacy been able to supply the current dose? Has the out-of-pocket cost changed? Does the patient know whom to contact if there is a gap? An interruption caused by coverage has a different explanation from a decision to stop because the burden outweighs the benefit. Documenting the reason makes it easier to choose a next step and to revisit that decision later.
Discuss maintenance while treatment is going well
SURMOUNT-4 studied adults without diabetes who completed a 36-week open-label lead-in with tirzepatide, a dual GIP and GLP-1 receptor agonist. From randomization through the following 52 weeks, participants who continued tirzepatide lost a further 5.5% on average, while those switched to placebo gained 14.0% relative to their weight at randomization [2]. The design makes the study informative about withdrawal among people who reached randomization after the lead-in. Its percentages should be read in that context.
This is a conversation worth having before an interruption. Ask how the patient feels about ongoing treatment and agree on what to monitor if it stops. A plan might specify which changes the patient wants to track, when to check in, and whom to contact before restarting after a prolonged gap. If weight returns, reviewing what happened to medication access, appetite, and daily routines gives the visit a more concrete starting point than an assumption about adherence.
Put emerging findings in their clinical context
Alcohol use disorder research illustrates how quickly a signal can become a headline. A small randomized trial reported reductions in some drinking outcomes with weekly semaglutide [3]. A subsequent 26-week trial in treatment-seeking adults with moderate to severe alcohol use disorder and coexisting obesity found a greater reduction in heavy drinking days with semaglutide than with placebo. Both groups received cognitive behavioral therapy [4]. The population, accompanying therapy, and outcome define what that result can support. Whether the findings generalize to people without obesity, persist after discontinuation, or extend to other substance use disorders requires separate evidence.
Biological aging claims require a similar distinction. A secondary analysis of a randomized trial in adults with HIV-associated lipohypertrophy reported changes in several DNA methylation measures of aging [5]. Those measures can inform research hypotheses. The analysis did not establish that treatment extends life or preserves function in a broader population. Those claims would require studies that track the relevant outcomes directly.
The studies that would help most at the next visit
Longer follow-up should capture how people function and feel alongside weight, and report what happens after interruptions caused by cost, supply, side effects, or preference. Practical studies could compare different approaches to follow-up after a gap and measure who can sustain treatment under ordinary conditions. The results would help clinicians and patients make decisions the original efficacy trials were never designed to answer.
At the end of a visit, I want the patient and clinician to agree on three things: what benefit they are looking for, what burden would prompt a change, and what to do if the next dose becomes difficult to obtain. GLP-1 trial results can inform that conversation. Follow-up is where we learn whether the plan still fits.
Author Bio












